Clinical Guidance on Drf Crefito for Knee Care
This guide explains Drf Crefito in an evidence-informed way for orthopedic decision-making. Background on the terms, why cartilage-focused and inflammation-aware assessment matters, and how clinicians typically structure workups are covered objectively. You’ll also find a requirements table, step-by-step clinician-style workflow, and FAQs to support safer, clearer conversations with suppliers and care teams.
Priority overview: how “Drf Crefito” fits into knee-oriented clinical decision-making
In orthopedic practice, Drf Crefito is best understood as a practical reference point for coordinating assessment, diagnostics, and conservative or procedural planning—particularly where knee pain, stability concerns, or cartilage-related symptoms are suspected. While the exact meaning of the phrase can vary by local use, the clinically useful approach is consistent: establish the problem accurately, define functional impact, and only then match the right treatment pathway and supply chain to the patient’s needs.
To keep your decisions safer and more transparent, this guide treats Drf Crefito as a framework keyword rather than a guaranteed diagnosis. It emphasizes objective evaluation, documented indications, and supplier accountability—so that clinicians, procurement teams, and patients can speak the same language without confusion.
In other words, think of Drf Crefito as a “decision discipline” label. It suggests that a structured knee workflow is being followed: history is taken carefully, the physical exam is performed systematically, the diagnostic plan is justified, and any intervention is selected based on clear indications rather than habit or incomplete information. When this discipline is implemented correctly, the same phrase can help standardize how teams interpret knee findings and how they procure the tools or kits that support the chosen clinical plan.
Why the keyword matters: “Crefito” language and the orthopedic workflow
Terms that resemble Crefito are often encountered in real-world orthopedic settings where professionals describe outcomes related to joint function, symptom reproducibility, or a structured clinical sequence (history → exam → imaging/labs → treatment planning). In many environments, “crepitus”-like concepts (audible or palpable joint sensations) may be discussed using shortened or localized wording. Depending on the clinic, “Crefito” may be used informally to capture the idea that a knee is producing a sensation during movement—sometimes in the context of degenerative disease, sometimes after an injury, and sometimes with coexisting soft-tissue pathology.
From an industry expert perspective, the key value is not the term itself but the workflow discipline it implies:
- Align symptom description with exam findings (not just imaging).
- Confirm indications before selecting any procedural option.
- Ensure supplier documentation supports clinical use requirements.
- Plan monitoring for response and safety.
To translate this into practical knee care, a team should treat the keyword as a prompt to ask: “What are we hearing or feeling, what does it mean in this specific patient, and what is the safest next step?” For example, a patient reporting audible clicking with pain could be experiencing osteoarthritis, but it might also reflect meniscal pathology, patellofemoral tracking issues, ligament instability, or even synovial irritation. The correct interpretation affects everything downstream—imaging selection, conservative versus procedural escalation, and the kind of interventions or devices that could be appropriate.
In procurement contexts, the same discipline applies: the team should avoid purchasing a knee procedure kit or related accessories based only on a vague mention of “crepito/crefito.” Instead, procurement should request enough clinical context so the delivered kit matches the intended procedure and is labeled appropriately for that intended use. The clinical workflow and the supply workflow must be aligned.
What clinicians typically evaluate when knee symptoms are suspected
For any knee-focused case where a keyword like Drf Crefito is used as a reference, clinicians generally prioritize these categories:
- History: onset pattern (gradual vs. sudden), mechanical features (locking/giving way), morning stiffness duration, activity triggers, and prior treatments.
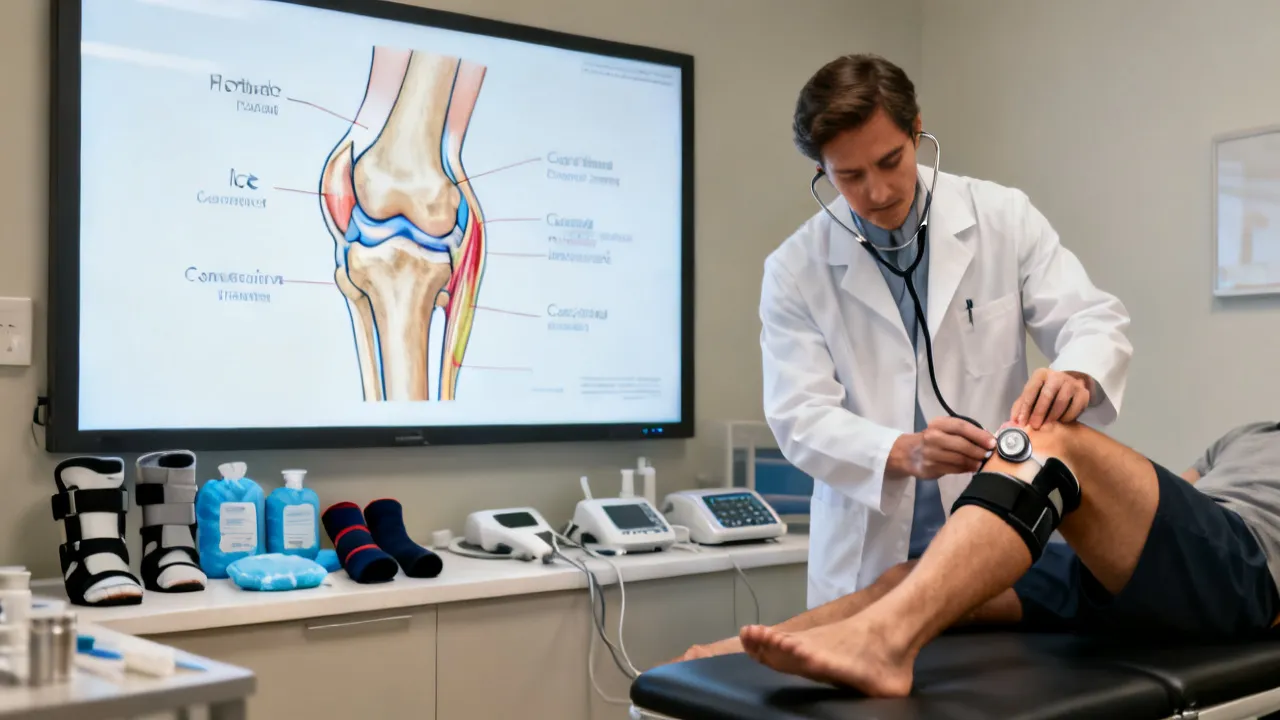
- Physical exam: range of motion, alignment, tenderness localization, stability testing, and assessment of joint sounds/sensation when relevant.
- Imaging strategy: X-ray for structural clues, MRI selectively when differential diagnosis requires it.
- Red flag screening: infection risk, inflammatory arthritis patterns, or acute neurovascular concerns.
- Functional impact: gait tolerance, stairs, squatting/bending capacity, work limitations, and pain-related medication needs.
These steps mirror widely accepted orthopedic reasoning used across musculoskeletal care settings. They also reduce the risk of mismatching products or interventions to symptoms that have different root causes. When a team uses Drf Crefito as a “workflow cue,” it should not shortcut those steps. Instead, it should help ensure they are performed in a consistent order with adequate documentation.
To make this more concrete, consider several common knee symptom patterns and what clinicians often look for:
- Gradual pain with activity (e.g., worse on stairs, better with rest) commonly leads clinicians to consider osteoarthritis or patellofemoral pain syndromes. Clinicians often correlate crepitus-like sensations with exam findings such as joint line tenderness, alignment deviations, or reduced range of motion.
- Sudden swelling after an injury prompts evaluation for internal derangement, ligament injury, fracture risk, or inflammatory flare. Here, joint sounds may exist but the priority is identifying urgent or structural problems.
- Mechanical locking (true locking rather than transient catching) often increases suspicion for meniscal tear or displaced cartilage fragments. Crepitus may occur, but the mechanistic focus shifts.
- Diffuse morning stiffness and swelling in multiple joints may suggest inflammatory arthritis. A procedure kit selection based on a crepitus-like concept alone would be inappropriate without proper rheumatologic assessment.
In all patterns, the “Drf Crefito” mindset is to connect symptoms to mechanisms through evidence-based evaluation. That connection is what enables safe and effective treatment planning.
Industry lens: procurement and supplier considerations tied to clinical intent
When orthopedic centers or suppliers mention terms like Drf Crefito, it can influence procurement decisions—especially if purchasing is tied to procedural kits, instrumentation, or accessory components used in knee-related interventions. From a quality-management standpoint, procurement should be evidence- and documentation-driven.
Rather than assuming a single keyword guarantees a specific outcome, teams typically ask:
- What exactly is being supplied (device family, accessory set, or clinical workflow component)?
- What is the intended use statement and labeling?
- What regulatory status applies in the jurisdiction of use?
- What training or competency is required for safe adoption?
- What documentation is available (IFU, traceability, lot records, sterilization guidance)?
- What post-procedure monitoring or follow-up pathway is recommended?
This approach aligns with widely recognized medical device quality principles and helps protect patient safety while supporting predictable clinical outcomes. Procurement is not just about “having the kit ready.” It’s about ensuring that the right kit is matched to the right patient context, the right clinician competence level, and the right procedural protocol.
To expand the procurement rationale, consider common real-world failure modes in medical supply chains:
- Specification drift: The clinical team’s needs change (different device size range, different procedural variant), but the procurement template stays the same. The result is a mismatch between the kit and the procedure.
- Labeling/IFU mismatch: The kit might be intended for one procedural indication but used informally for another. This can increase risk and create compliance issues.
- Inadequate sterilization compatibility: Some components require particular handling or sterilization methods. Without correct sterilization guidance, sterility assurance can be compromised.
- Training gaps: Even if the device is “compatible,” the team might not be trained to use it properly (setup, assembly, handling, documentation). The safety risk can be clinical, not just administrative.
- Traceability and recall readiness: If lot/serial records are not captured, it becomes harder to manage any quality incident or recall event.
The Drf Crefito framework helps prevent these failure modes by encouraging documentation-backed decisions. Instead of interpreting “Crefito” as a direct diagnosis, teams interpret it as a cue that structured evaluation must be paired with supply verification.
Quality and safety: what reliable orthopedic guidance emphasizes
Orthopedic literature commonly stresses that knee pain—especially in adults—is multifactorial. For example, osteoarthritis management generally begins with conservative care (exercise, education, weight optimization where applicable, and appropriately selected analgesia), while procedures are considered when symptoms persist or structural/functional deficits warrant further action. Major bodies such as the American College of Rheumatology (ACR) and the Arthritis Foundation publish guidance on nonpharmacologic and pharmacologic strategies for osteoarthritis, which is often used as a backbone for conservative planning. The emphasis is on patient-centered care, clear indications, and structured follow-up.
For clinical teams, a keyword like Drf Crefito should never replace diagnostic reasoning. It should function as a reminder to keep decisions traceable to symptoms, examination, and validated treatment pathways.
To reinforce the safety logic, consider how conservative-first principles reduce risk. Conservative treatment typically offers symptom relief and functional improvement with fewer procedural complications. It also provides time to refine the diagnosis if the initial working hypothesis is uncertain. For example, if a patient initially looks like osteoarthritis but fails to improve and develops new signs (progressive instability, inflammatory features, neurologic symptoms), that failure is not necessarily “treatment failure”—it can be diagnostic feedback. It prompts reassessment rather than blind continuation of the same pathway.
In practice, a Drf Crefito-oriented workflow that honors quality and safety usually includes:
- Clear baseline outcomes: pain scores, function measures, and range of motion or stability descriptors documented before intervention.
- Risk screening: infection signs, inflammatory pattern clues, fracture risk, and red-flag neurological symptoms identified early.
- Informed consent readiness: documentation of what is being attempted, why it is appropriate, and what alternative pathways exist.
- Appropriate escalation criteria: a plan for when to progress from conservative therapy to procedural care based on objective response.
Market realities: how “price” and “supplier details” should be handled
You mentioned price information and supplier details, but the prompt provided does not include specific numeric values, manufacturer names, or locality pricing. In professional procurement practice, the right way to use price data is to treat it as part of a verified cost-and-compliance comparison rather than a substitute for clinical suitability.
Accordingly, this article provides a structured comparison method you can apply once you have:
- the exact item description (device type, size range, kit composition, or service bundle),
- the supplier’s documentation packet, and
- the price quote for the intended volume and lead time.
This method supports cost transparency while reducing the chance of purchasing “the wrong thing in the right price range.” In healthcare procurement, “lowest price” is rarely an optimal strategy unless it is supported by “lowest total risk” and “best documented match to intended use.” When a kit is cheaper but lacks critical components, has incomplete IFU information, or cannot be integrated into sterile workflows properly, the hidden costs can exceed the apparent savings—through delay, re-procurement, staff re-training, or quality incidents.
To make price comparisons more meaningful, many organizations use a “value scorecard” rather than price-only evaluation. While the exact formula varies, the concept is consistent: combine clinical fit, documentation completeness, training support, delivery reliability, and total cost of ownership (including any consumables, handling, and service). In that framework, a keyword like Drf Crefito becomes a reminder to evaluate fit to workflow rather than just procurement cost.
Step-by-step clinician-style workflow aligned with Drf Crefito use
Below is a practical workflow that teams often use in knee care planning. It assumes Drf Crefito is acting as a shorthand reference for structured knee assessment and selection of the appropriate care pathway.
Requirements and conditions (comparison table)
| Category | What to verify | Why it matters |
|---|---|---|
| Clinical indication | Symptom pattern, exam findings, functional limitations, and differential diagnosis | Prevents mismatching interventions to causes of pain |
| Diagnostic documentation | Imaging/lab results where indicated; standardized notes | Enables continuity of care and safer selection |
| Intended use alignment | Device or kit labeling/IFU matched to the plan | Supports correct technique and reduces risk |
| Supplier documentation | Traceability, lot/serial records, sterilization guidance (if applicable) | Ensures quality control and accountability |
| Training requirements | Competency, onboarding, and procedural protocol readiness | Improves consistency and safety |
| Monitoring plan | Follow-up schedule and outcome measures (function, pain, stability) | Enables early detection of complications or non-response |
Step-by-step guide (applied to Drf Crefito-oriented knee care)
- Clarify the patient’s goal: pain reduction, return to activity, improved stability, or functional restoration—document it in neutral, measurable terms.
- Screen for red flags: consider infection, inflammatory conditions, or acute injury patterns that change urgency and treatment direction.
- Perform a structured knee exam: assess range of motion, alignment, tenderness, stability, and relevant joint sensations.
- Decide on diagnostics: use imaging/labs selectively based on clinical need and differential diagnosis rather than reflexively.
- Map symptoms to likely mechanisms: degenerative changes, mechanical irritation, soft-tissue causes, or mixed pain sources.
- Select the care pathway: conservative first where appropriate, or a procedural plan when indications are clear and risks are controlled.
- Procure with documented intended use: ensure the supplier’s materials match the clinical plan, including labeling and traceability.
- Confirm training and protocol: verify that the team is prepared for correct application and sterile/handling steps where applicable.
- Set follow-up and outcome tracking: use standardized functional and symptom markers so improvements (or lack of them) are interpretable.
- Review and iterate: if response is inadequate, reassess diagnosis and reconsider the plan rather than forcing the same approach.
To deepen this workflow, consider how teams typically operationalize each step in documentation and daily practice. The idea is to ensure that every action is tied to measurable clinical logic.
Step 1: Clarify the patient’s goal should include not only “less pain” but also the timeframe and function. For instance, “I want to walk for 30 minutes without needing to stop” is more actionable than “I want it to hurt less.” Baseline function might be documented as distance walked, stair tolerance, or gait quality. A keyword like Drf Crefito can be used to remind teams to write measurable outcomes before selecting any procedural or device-based plan.
Step 2: Screen for red flags is not just a checkbox. Clinicians should identify infection risk (fever, warmth, systemic symptoms), inflammatory disease patterns (swelling, multiple joints, prolonged morning stiffness), and neurovascular compromise (numbness, weakness, vascular symptoms) as these can change urgency and treatment direction. If a red flag is present, the knee “workflow discipline” becomes even more critical: procedural decisions may need to be delayed while urgent workup proceeds, and procurement should avoid assumptions about the device pathway.
Step 3: Perform a structured knee exam should capture both objective findings and patient-reported symptom triggers. Exam elements can include alignment evaluation, palpation for tenderness (joint lines, patellar facets, periarticular structures), assessment of range of motion with pain, and stability testing. When joint sounds or sensations are relevant, documenting when they occur (e.g., during flexion at certain degrees, or with weight-bearing) supports later interpretation.
Step 4: Decide on diagnostics ties the decision to differential diagnosis. A typical conservative approach might start with X-ray if osteoarthritis is suspected and structural assessment would change management. MRI may be reserved for cases where suspected internal derangement, surgical planning considerations, or complex differential diagnosis requires it. Labs may be appropriate if inflammatory or infectious etiologies are suspected. The “Drf Crefito” discipline here is to avoid over-imaging or under-documenting. If the team cannot justify why imaging is being ordered, it can be difficult to justify subsequent procedural choices.
Step 5: Map symptoms to likely mechanisms often involves pattern recognition combined with clinical reasoning. Mechanical symptoms (locking, catching) suggest one category; diffuse swelling and systemic symptoms suggest another; instability or giving way suggests ligament involvement; and crepitus-like sensations with pain on loading can fit osteoarthritis patterns. This step turns descriptive language into mechanism-based hypotheses, which then informs treatment selection.
Step 6: Select the care pathway uses mechanism-based hypotheses and evidence-based guidelines. Conservative-first strategies might include exercise therapy, education, activity modification, assistive devices, weight management where appropriate, and analgesics consistent with patient comorbidities. Procedures may be considered when symptoms persist despite conservative care or when functional deficits warrant escalation. Importantly, procedural choices should be tied to the mechanism and documented indication, not to a keyword alone.
Step 7: Procure with documented intended use is where Drf Crefito can have procurement leverage. If procurement receives only a vague instruction (“We need the crepito kit”), it is difficult to ensure correct supply matching. Instead, procurement should receive the intended procedure name, the clinical indication, the relevant patient factors (as allowed), and the device/kit specification. Documentation should include labeling and IFU details that support safe use.
Step 8: Confirm training and protocol reduces risk created by variation in technique. Even small differences in setup, handling, or time sequencing can influence outcomes and safety. Training confirmation should include not only initial competency but also readiness of the team on the day of the procedure. For example, ensuring the availability of correct sterile technique supplies and verifying that documentation systems are ready for traceability fields are all part of clinical and operational readiness.
Step 9: Set follow-up and outcome tracking should include timepoints that match the expected trajectory of response. If the intervention is intended to reduce pain or improve function, outcome measures must be selected in alignment with that intention. Teams might track pain scores, walking tolerance, stair performance, range of motion, stability symptoms, and adverse events. The key is consistent baseline and consistent follow-up measurement.
Step 10: Review and iterate ensures that poor response leads to reconsideration rather than persistence. A patient who fails to improve may require reassessment of diagnosis, reconsideration of comorbidities, evaluation for complications, or a different treatment pathway. The “Drf Crefito” mindset supports clinical humility: the workflow is disciplined, but it remains responsive to evidence generated by the patient’s course.
Comparing “Drf Crefito” mentions across care settings
Because Drf Crefito and Crefito-like terminology may be used differently across clinics, it can help to compare how a facility operationalizes the keyword. For example:
- Clinical teams may use it to signal a structured knee evaluation checklist and follow-up cadence.
- Suppliers may use it to describe a kit composition or workflow inclusion that supports an orthopedic procedure.
- Patients may encounter it as a shorthand label for what they were told about joint sounds, sensation, or a planned intervention.
When communication is inconsistent, misunderstandings occur. The safest path is to translate the keyword into plain language: “What is the diagnosis working hypothesis? What is the intended treatment? What is the monitoring plan?”
To further clarify cross-setting communication, here are examples of how the same keyword can lead to different interpretations:
- A clinic might say “crepito present,” meaning crepitus on exam. Procurement might hear “crepito kit,” implying a device is needed. Without clarification, procurement might provide supplies that do not match the exam findings or the intended clinical plan.
- A supplier might mention “crepito” in product marketing as a symptom-related use case. Clinicians still need to link the product use to labeled indications, contraindications, and patient-specific factors.
- A patient might interpret the term as a formal diagnosis and ask directly for a procedure. Clinicians should avoid creating diagnostic certainty from informal terminology.
Therefore, the translation step—moving from keyword to clinical intent—is essential. Teams should standardize phrasing in internal communication. Instead of repeating Drf Crefito, they should record: “Observed finding: [crepitus/catching/etc.]. Clinical hypothesis: [osteoarthritis vs internal derangement]. Next action: [conservative plan, imaging, or procedure].” This makes communication robust across stakeholders.
FAQs
1) What does “Drf Crefito” mean in knee care?
In most practical contexts, Drf Crefito functions as a shorthand reference used by clinicians or procurement teams to indicate a structured approach to knee evaluation and related care planning. Its exact meaning can vary, so the key is to clarify the concrete clinical steps it is associated with—diagnosis workflow, intended use of any kit or device, and monitoring requirements.
If you are trying to operationalize it in an actual care plan, ask for the “translation” into plain clinical intent: What problem is being addressed, what is the evidence used to justify next steps, and what outcomes will confirm success?
2) Is “Crefito” the same as a specific medical diagnosis?
No. Crefito-like terminology is often discussed in relation to sensations or joint findings during exams. It should be treated as descriptive language, not a standalone diagnosis. A proper assessment should connect findings to a differential diagnosis and an agreed care plan.
For instance, crepitus-like findings can be present in osteoarthritis, but also in patellofemoral pain syndromes or other conditions. Therefore, diagnosis must be determined by the full clinical picture: history, exam, and appropriate imaging/labs as needed.
3) How should price information be evaluated for knee-related supplies or kits?
Price should be compared only after you confirm the exact item specification, intended use, regulatory/labeling documentation, sterilization or handling requirements (when relevant), and training prerequisites. The cheapest quote is rarely the safest choice if it omits required documentation or does not match the clinical plan.
In practice, evaluate total value rather than unit price. If one supplier’s kit requires additional consumables to be clinically complete, the apparent savings may vanish. If another supplier provides superior documentation support, reduces onboarding time, or improves traceability, it may reduce downstream costs and risk—creating better overall value.
4) What supplier details are most important for compliance and safety?
Focus on traceability (lot/serial records), intended use statements and labeling/IFU, quality documentation, and clear guidance for storage/handling and sterile workflows when applicable. Also verify that the supplier can support implementation training or protocol alignment.
Additionally, ensure that the supplier can provide any required documentation for your facility’s quality system (e.g., incoming inspection criteria, acceptance testing, sterilization validation references if relevant). The ability to support a recall process with rapid traceability can be an overlooked safety feature.
5) Who should decide whether a procedure is necessary?
The decision should be made by the treating clinician based on history, exam, and appropriate diagnostics, together with the patient’s functional goals and risk tolerance. Procurement teams can support availability of appropriate items, but they should not replace clinical judgment.
When shared decision-making is practiced well, patients understand the rationale for conservative-first strategies and the conditions under which procedural options become appropriate. The team should not present procurement availability as the driver of clinical decisions.
6) What outcomes should be tracked after knee treatment?
Typically, teams track pain changes, functional ability (stairs, walking tolerance, activity return), range of motion, and any adverse events or complications. Consistent follow-up documentation is essential for interpreting whether the care pathway is effective.
Outcome tracking should be time-bound. For example, early follow-up might focus on pain and adverse events, while later follow-up might focus on function and longer-term stability or mobility. Without time-appropriate measures, it becomes difficult to determine whether the intervention is working or whether it is delayed response.
7) What if symptoms improve but diagnosis is uncertain?
Improvement is a valuable signal, but unclear diagnosis can still matter for long-term management. Clinicians may refine the differential diagnosis over time, adjust the treatment plan, and continue monitoring to ensure the condition is not progressing in a way that requires escalation.
In such cases, the “Drf Crefito” workflow can be helpful because it emphasizes documentation and reassessment rather than anchoring too early on a single label.
Evidence-informed context: conservative-first principles and why they matter
Major clinical guidance for knee osteoarthritis and similar degenerative knee conditions commonly emphasizes conservative-first strategies. For example, the American College of Rheumatology (ACR) and Arthritis Foundation provide guidance on nonpharmacologic and pharmacologic management that many orthopedic and rheumatology teams use as a basis for shared decision-making. The overarching principle is to combine symptom relief with functional improvement while maintaining safety and realistic expectations.
In practice, this means a Drf Crefito-oriented workflow should prioritize:
- education and activity modification where appropriate,
- exercise and strength/neuromuscular conditioning,
- careful analgesic selection aligned to patient needs, and
- procedural escalation only when indicated.
Even when a keyword is used in local practice, the care path should remain consistent with evidence-based principles and sound clinical reasoning.
To expand on conservative-first strategy logic, it helps to understand why exercise and education are often foundational. In many knee conditions, symptoms are influenced by biomechanics, muscle strength (especially quadriceps and hip stabilizers), neuromuscular control, and load management. Education helps patients understand how to modify activities without over-restricting or under-using the joint. Analgesics and topical options can support participation in exercise and improve short-term tolerability, but they must be chosen with comorbidities and contraindications in mind.
Procedural escalation can be appropriate in selected scenarios, but it is not a substitute for conservative measures. When procedures are used, documentation should include: why the procedure is indicated, what mechanism is targeted, what risks are explained, and what outcomes are expected. The “Drf Crefito” mindset supports that by tying decisions to the diagnostic workflow rather than to an informal keyword.
Where localization helps without overselling: communicating in everyday terms
If you are working with patients or staff in English-speaking orthopedic settings, avoid jargon in conversations about Drf Crefito. Instead, translate it into operational questions:
- “What are we trying to find out?”
- “What are we trying to improve—pain, stability, or function?”
- “What do we need to document to choose the right next step?”
- “How will we tell if it’s working?”
This keeps discussions grounded and reduces the risk that the keyword becomes a substitute for informed consent or clinical clarity.
From a patient communication perspective, it can also help to describe findings in plain language. For example, rather than using “Crefito” or “crepitus” as the centerpiece, clinicians can explain: “When your knee moves, we feel or hear grinding/clicking. That can happen for several reasons. Our job today is to figure out which reason fits your symptoms and exam.” This keeps the focus on evaluation and shared understanding.
From a staff communication perspective, internal documents should standardize terminology. If a chart contains “Drf Crefito” as a tag, it should also include structured fields: pain score, functional limitation, exam findings, and the plan. That ensures the tag is not a placeholder but a routing mechanism to the real clinical content.
Reference sources (for guidance concepts)
- American College of Rheumatology/Arthritis Foundation: osteoarthritis management guidance (nonpharmacologic and pharmacologic recommendations). (Use the latest published update available in your jurisdiction and clinical setting.)
- Orthopedic and rheumatology clinical practice principles summarized in major consensus and guideline publications on knee osteoarthritis evaluation and staged management.
Note: When using any guideline or evidence in practice, clinicians should apply local regulatory requirements and consider patient-specific comorbidities, contraindications, and clinical judgment.
To keep the workflow aligned with evidence and safety, teams should also consider how local policies influence decisions. For example, local formularies can affect medication availability; local imaging protocols can determine when and how MRI is authorized; and local device regulations can influence procurement and labeling requirements. A Drf Crefito-oriented workflow remains the same in concept, but its implementation must respect these jurisdictional constraints.
Closing guidance: turning “Drf Crefito” into clearer decisions
Ultimately, Drf Crefito should be treated as a cue for disciplined, documentation-backed knee care planning—linking symptoms to exam findings, aligning any recommended intervention with intended use requirements, and tracking outcomes with a transparent follow-up strategy. When price and supplier information are incorporated, they should enhance—not replace—clinical decision-making.
If you share your specific product type (e.g., kit category, device family), your supplier’s documentation fields, and the jurisdiction where the care will be delivered, I can help you build a tighter comparison matrix tailored to your exact scenario and purchasing workflow.
To make that final step even more practical, the best input package for tailoring would typically include: (1) the exact clinical context where Drf Crefito is being referenced in your documents, (2) whether it is used as an exam shorthand, a procurement shorthand, or both, (3) the intended procedure type (if any), and (4) the decision point at which procurement becomes involved. With those details, you can transform the keyword into a standardized, cross-functional decision pathway that improves patient safety and reduces procurement ambiguity.
-
1

Explore the Tranquil Bliss of Idyllic Rural Retreats
-
2
Unlock the Full Potential of Your RAM 1500: Master the Art of Efficient Towing!
-
3
Leveraging High-Interest CDs for Optimized Investment Returns
-
4
How to Take Advantage of Debt Consolidation Loans: Key Strategies
-
5
Understanding Debt Consolidation Loans: Weighing Advantages and Disadvantages